

1L HER2- GC/GEJC OS results
1L HER2- GC/GEJC: OS in PD-L1 ≥1%
Durable survival benefit with TEVIMBRA + chemotherapy1,2
Primary analysis: 15.0 months mOS with TEVIMBRA + chemotherapy (95% CI: 13.3-16.7) vs 12.8 months with placebo + chemotherapy (95% CI: 12.1-14.1); HR: 0.78 (95% CI: 0.67-0.90)*
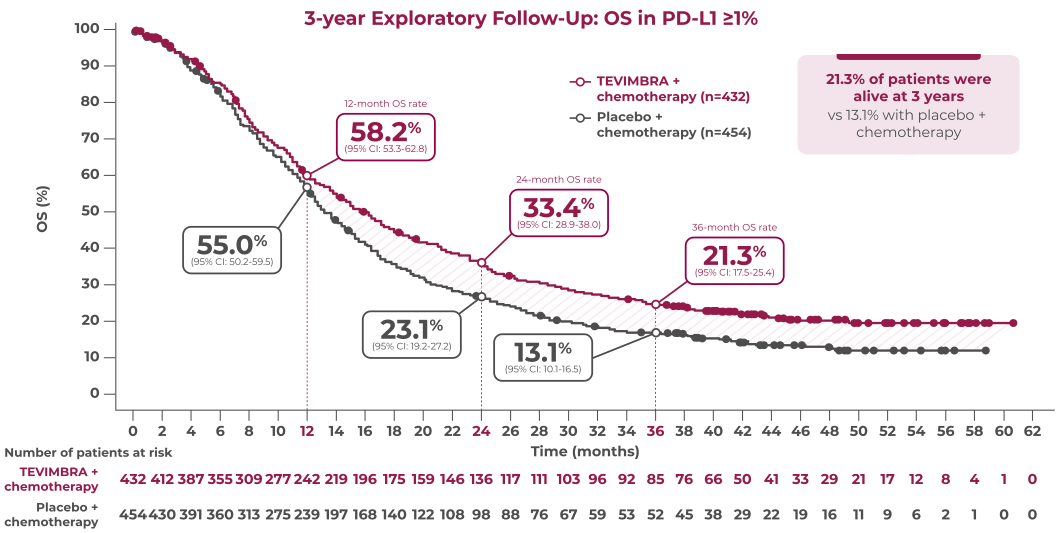
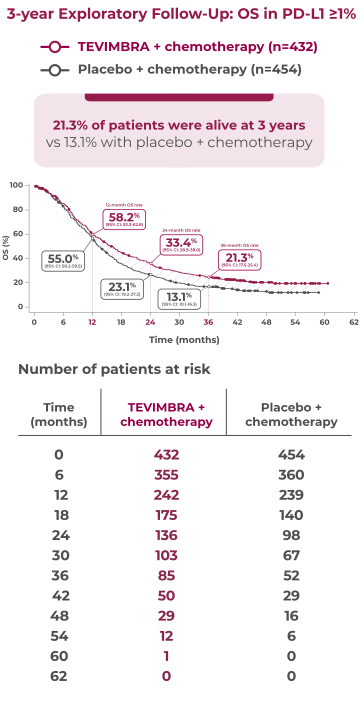
Image description
Primary analysis: In patients with a PD-L1 score ≥1%, TEVIMBRA + chemotherapy demonstrated 15.0 months median overall survival (95% CI: 13.3-16.7) vs 12.8 months with placebo + chemotherapy (95% CI: 12.1-14.1); HR: 0.78 (95% CI: 0.67-0.90).
3-year exploratory follow up: Among patients with a PD-L1 score ≥1%,
- At 3 years TEVIMBRA + chemotherapy (n=432) had a 21.3% overall survival rate (95% CI: 17.7-25.4) vs 13.1% (95% CI: 10.1-16.5) with placebo + chemotherapy (n=454)
- At 2 years, TEVIMBRA + chemotherapy (n=432) had a 33.4% overall survival rate (95% CI: 28.9-38.0) vs 23.1% (95% CI: 19.2-27.2) with placebo + chemotherapy (n=454)
- At 1 year, TEVIMBRA + chemotherapy (n=432) had a 58.2% overall survival rate (95% CI: 53.3-62.8) vs 55.0% (95% CI: 50.2-59.5) with placebo + chemotherapy (n=454)
Limitation: The 3-year OS analysis was exploratory in nature and was not powered to show statistical significance. Landmark OS rates were estimated using the Kaplan-Meier method. No definitive conclusions can be drawn.
NCCN
preferred
1l gc/gejc
PD-L1 ≥1
National Comprehensive Cancer Network® (NCCN®) recommends tislelizumab-jsgr (TEVIMBRA®) in combination with fluoropyrimidine and oxaliplatin or cisplatin, for adults with 1L, unresectable, locally advanced, recurrent, or metastatic, HER2-negative GC or GEJ adenocarcinoma whose tumors express PD-L1 (≥1).3,4*
.
Expert Review of Overall Survival Data and NCCN Recommendations
Subgroup analysis of OS in 1L HER2- GC/GEJC (PD-L1 ≥1%)
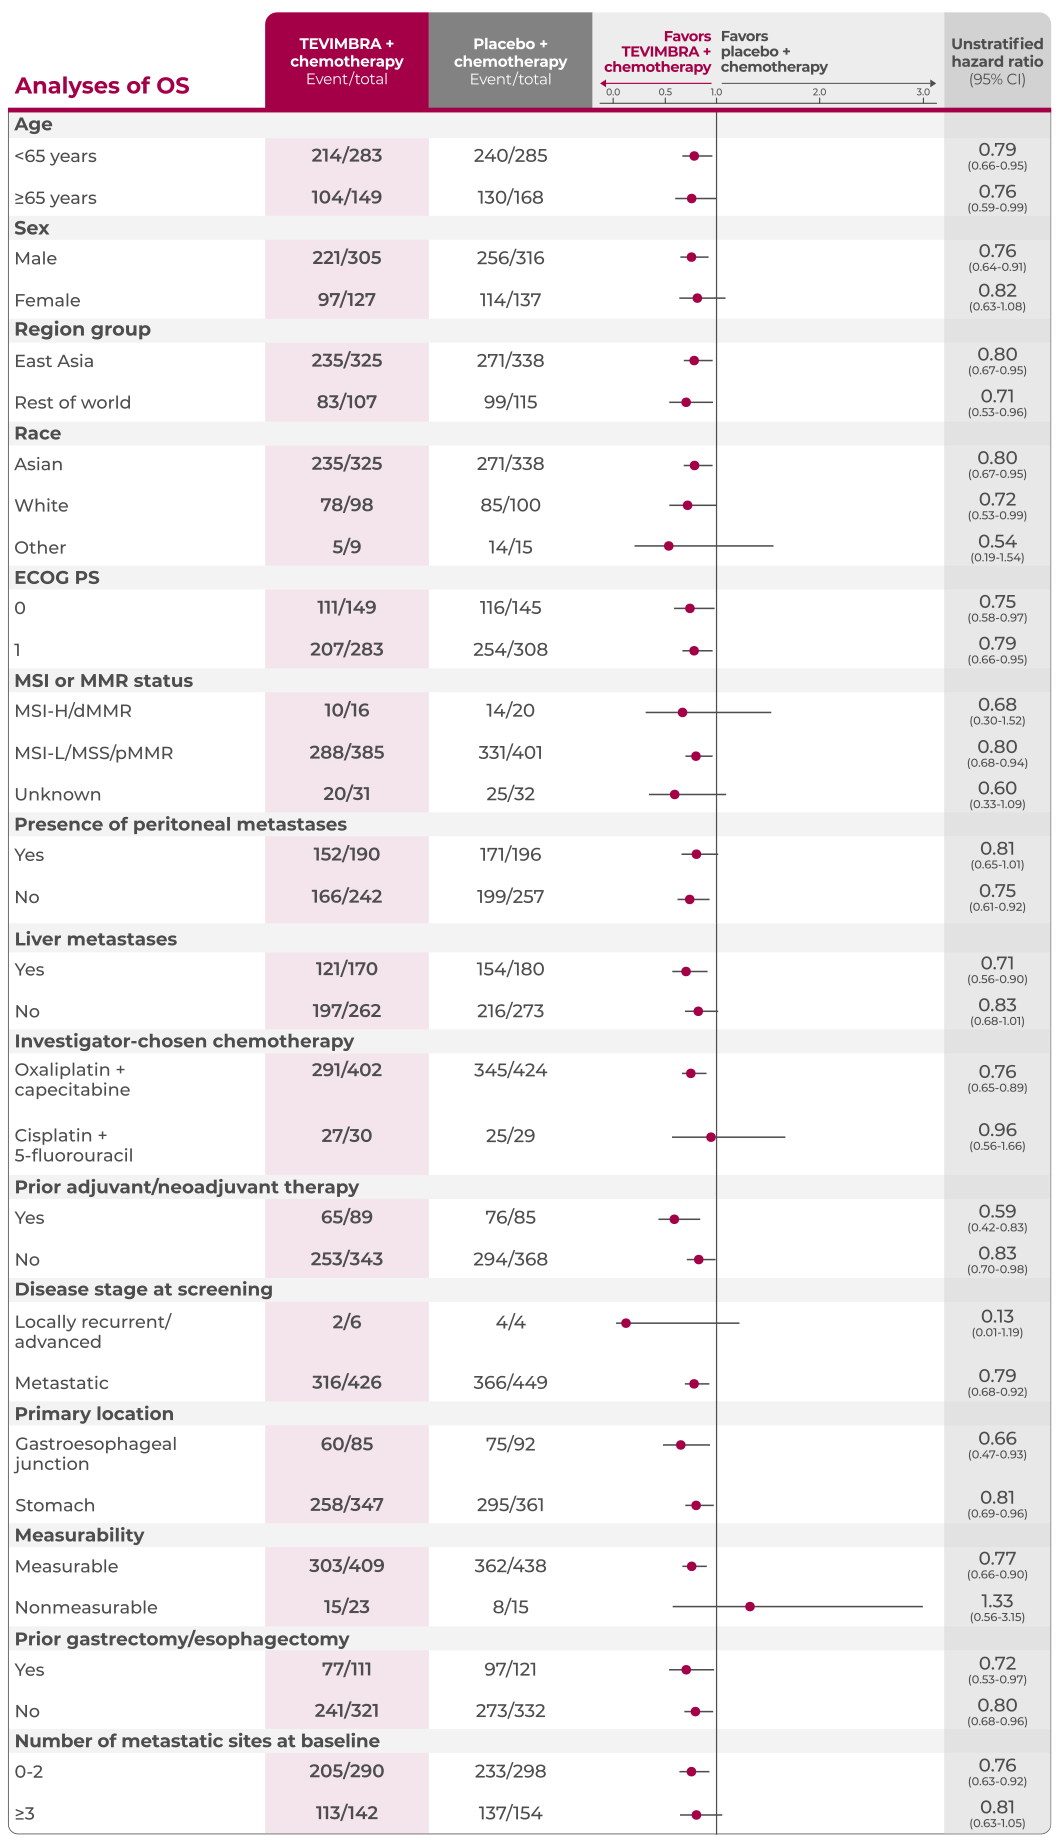
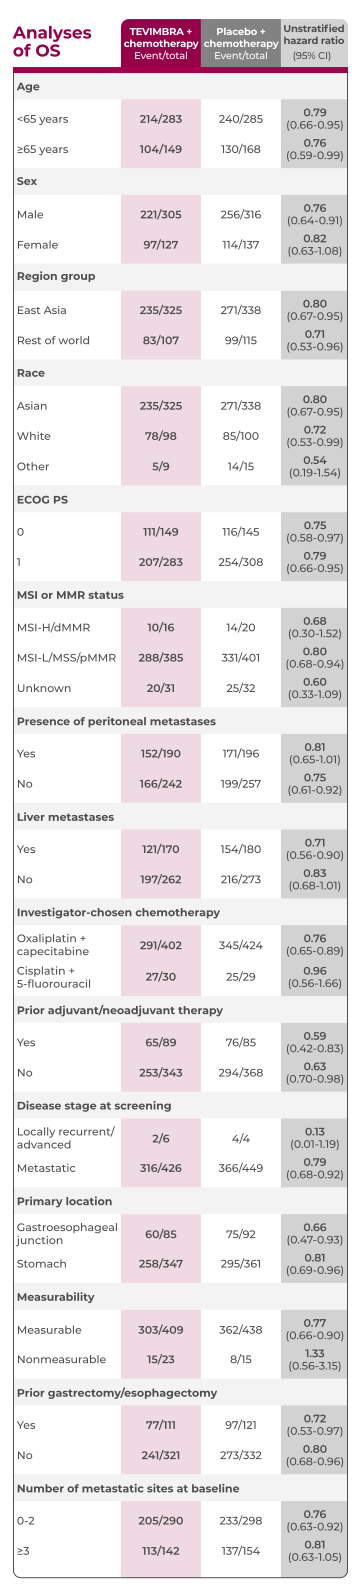
A consistent trend in overall survival favoring TEVIMBRA + chemotherapy across multiple key subgroups2
TEVIMBRA + chemotherapy reported overall survival across common sites of metastases5-8
- First and only immunotherapy and chemotherapy treatment with positive overall survival data reported for patients with peritoneal metastases in trials using a PD-L1 score cutoff of ≥1%5-8
Analyses of OS
.
Expert Opinion on RATIONALE-305 OS Subgroup Analyses
Frequently Asked Questions
What was the overall survival with TEVIMBRA in patients with 1L HER2- advanced GC/GEJC and PD-L1 scores ≥1%?
TEVIMBRA + chemotherapy is proven to extend overall survival in patients with 1L HER2- advanced GC/GEJC and PD-L1 scores ≥1%. TEVIMBRA + chemotherapy demonstrated 15.0 months median overall survival vs 12.8 months median overall survival with placebo + chemotherapy. The hazard ratio was 0.78 with a 95% confidence interval of 0.67-0.90.1
What were the 3-year results for TEVIMBRA in patients with 1L HER2- advanced GC/GEJC scores ≥1%?
In the 3-year exploratory analysis, TEVIMBRA + chemotherapy provided sustained overall survival for 3 years. 21.3% of patients were still alive at 3 years with TEVIMBRA + chemotherapy vs 13.1% with placebo + chemotherapy.2
Limitation: The 3-year OS analysis was exploratory in nature and was not powered to show statistical significance. Landmark OS rates were estimated using the Kaplan-Meier method. No definitive conclusions can be drawn.
What were the results for TEVIMBRA across patients with peritoneal metastases in 1L HER2- advanced GC/GEJC?
Limitation: Post-hoc subgroup analyses were not statistically powered and were descriptive only. No definitive conclusions can be drawn.
What are the NCCN recommendations for using tislelizumab-jsgr (TEVIMBRA®) in 1L HER2- advanced GC/GEJC?
*Category 1 Preferred for patients whose tumors express PD-L1 (≥5).
†PD-L1 expression levels as determined by CPS.
References: 1. TEVIMBRA. Prescribing Information. BeOne Medicines USA, Inc.; 2026. 2. Moehler M, Oh DY, Kato K, et al. Adv Ther. 2025;42(5):2248-2268. 3. Referenced with permission from the NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) for Esophageal and Esophagogastric Junction Cancers V.3.2026. © National Comprehensive Cancer Network, Inc. 2026. All rights reserved. Accessed February 25, 2026. To view the most recent and complete version of the guideline, go online to NCCN.org. NCCN makes no warranties of any kind whatsoever regarding their content, use or application and disclaims any responsibility for their application or use in any way. 4. Referenced with permission from the NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) for Gastric Cancer V.3.2026. © National Comprehensive Cancer Network, Inc. 2026. All rights reserved. Accessed February 25, 2026. To view the most recent and complete version of the guideline, go online to NCCN.org. 5. Rha SY, Oh DY, Yañez P, et al; KEYNOTE-859 Investigators. Lancet Oncol. 2023;24(11):1181-1195. doi:10.1016/S1470-2045(23)00515-06 Published correction appears in Lancet Oncol. 2024;25(12):e626. doi:10.1016/S1470-2045(24)00650-8 6. Janjigian YY, Ajani JA, Moehler M, et al. J Clin Oncol. 2024;42(17):2012-2020. doi:10.1200/JCO.23.01601 7. Shitara K, Moehler M, Ajani J, et al. Poster presented at: American Society of Clinical Oncology Gastrointestinal Cancers Symposium; January 18-20, 2024; San Francisco, CA. Poster Bd E6. 8. Sonbol MB, Rha SY, Xu RH, et al. Abstract and poster presented at: ASCO Gastrointestinal Cancers Symposium; January 8-10, 2026. San Francisco, CA. Abstract 378, poster D9.